Laparoscopic PUJ Obstruction Surgery: Procedure, Instruments, Benefits & Recovery
Laparoscopic PUJ Obstruction Surgery is a minimally invasive urological procedure used to treat selected patients with pelvi-ureteric junction obstruction. The operation, commonly called laparoscopic pyeloplasty, aims to restore urine drainage from the kidney into the ureter.
PUJ obstruction occurs when the connection between the renal pelvis and ureter becomes narrowed or blocked. Consequently, urine may accumulate in the kidney and cause hydronephrosis.
Although some patients require surgery, others can be monitored depending on their symptoms, kidney function, and imaging findings.
This JDMeditech guide explains PUJ obstruction, laparoscopic pyeloplasty, surgical instruments, treatment options, benefits, complications, recovery, and frequently asked questions.
What Is PUJ Obstruction?
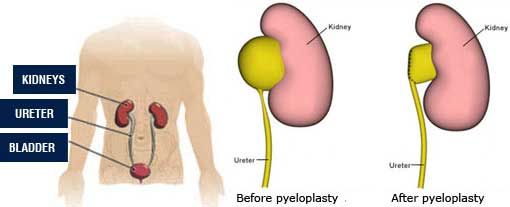
Pelvi-ureteric junction obstruction, also known as ureteropelvic junction (UPJ) obstruction, is a condition that restricts urine flow where the renal pelvis connects to the ureter.
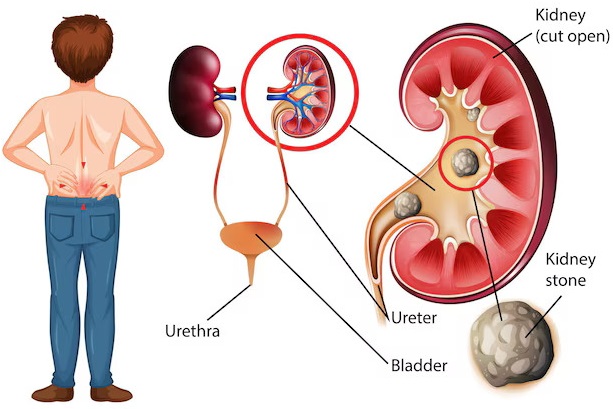
Normally, urine collects in the renal pelvis and passes through the ureter into the bladder.
However, narrowing at the junction can prevent efficient drainage. As a result, pressure may increase within the kidney.
Persistent obstruction may contribute to pain, urinary infections, hydronephrosis, and reduced kidney function.
Common Symptoms of PUJ Obstruction
- Flank or side pain
- Abdominal discomfort
- Recurrent urinary tract infections
- Blood in the urine
- Nausea or vomiting
- Hydronephrosis detected on ultrasound
- Kidney stones in some patients
- Reduced kidney function in advanced cases
However, some patients have no noticeable symptoms. In children, PUJ obstruction may be identified during prenatal or postnatal ultrasound examinations.
What Causes PUJ Obstruction?
1. Congenital Narrowing
Some patients are born with abnormal development of the ureteropelvic junction. This may interfere with normal urine drainage.
2. Crossing Blood Vessels
An accessory or crossing blood vessel may compress the junction and contribute to obstruction.
3. Scar Tissue
Previous inflammation, injury, or surgery can occasionally cause narrowing of the urinary drainage pathway.
4. Kidney Stones
Stones or associated inflammation may contribute to upper urinary tract obstruction.
5. Abnormal Ureteral Insertion
An unusual connection between the ureter and renal pelvis may affect drainage.
How Is PUJ Obstruction Diagnosed?
A urologist evaluates the patient’s symptoms, medical history, and kidney function.
Ultrasound is commonly used to identify hydronephrosis.
Depending on the clinical situation, CT urography or MRI may help define the urinary anatomy.
Furthermore, a diuretic renal scan, such as MAG3 renography, may help assess drainage and differential kidney function.
However, hydronephrosis alone does not always establish clinically significant obstruction.
Therefore, treatment decisions require assessment of symptoms, imaging, and kidney function together.
What Is Laparoscopic PUJ Obstruction Surgery?
Laparoscopic PUJ Obstruction Surgery is a minimally invasive reconstructive procedure that repairs narrowing between the renal pelvis and ureter.
The surgeon uses a laparoscope, specialized instruments, and small abdominal incisions to access the affected region.
In a commonly performed technique called Anderson-Hynes dismembered pyeloplasty, the narrowed segment is removed and the healthy ureter is reconnected to the renal pelvis.
However, surgical techniques vary according to patient anatomy and the cause of obstruction.
When Is Laparoscopic Pyeloplasty Recommended?
A urologist may recommend surgery when PUJ obstruction causes persistent symptoms or threatens kidney function.
Common considerations include:
- Recurrent or significant flank pain
- Progressive hydronephrosis
- Declining differential kidney function
- Recurrent urinary infections associated with obstruction
- Obstructed drainage on appropriate investigations
- Selected cases involving crossing vessels
However, stable patients without significant functional deterioration may be suitable for observation.
Treatment Options for PUJ Obstruction
1. Observation and Monitoring
Selected patients may undergo periodic ultrasound and renal function assessment without immediate surgery.
2. Open Pyeloplasty
Open pyeloplasty repairs the obstructed junction through a conventional surgical incision.
3. Laparoscopic Pyeloplasty
Laparoscopic pyeloplasty uses small incisions and specialized laparoscopic instruments to reconstruct the junction.
4. Robotic-Assisted Pyeloplasty
Robotic-assisted pyeloplasty uses a compatible robotic platform to support minimally invasive reconstruction.
5. Endopyelotomy
Endopyelotomy involves an internal incision of the narrowed junction in selected patients.
However, it generally has a lower long-term success rate than pyeloplasty and may be unsuitable when crossing vessels or other anatomical factors are present.
6. Temporary Urinary Drainage
In selected circumstances, a ureteral stent or percutaneous nephrostomy may be used to relieve obstruction before definitive treatment.
Types of Laparoscopic Pyeloplasty
1. Anderson-Hynes Dismembered Pyeloplasty
This technique removes the narrowed junction and reconnects the ureter to the renal pelvis.
It is widely used for PUJ obstruction, including selected cases with crossing vessels.
2. Non-Dismembered Pyeloplasty
Selected anatomical conditions may be treated using a reconstructive technique that does not completely separate the ureter from the renal pelvis.
3. Transperitoneal Laparoscopic Pyeloplasty
The surgeon accesses the kidney through the abdominal cavity.
4. Retroperitoneoscopic Pyeloplasty
The surgeon accesses the kidney through the retroperitoneal space, avoiding routine entry into the peritoneal cavity.
5. Robotic-Assisted Pyeloplasty
Selected centers use robotic assistance for reconstruction and intracorporeal suturing.
Comparison of PUJ Obstruction Surgical Approaches
| Feature | Open Pyeloplasty | Laparoscopic Pyeloplasty | Robotic Pyeloplasty |
|---|---|---|---|
| Access | Larger incision | Small incisions | Small incisions |
| Visualization | Direct surgical exposure | Camera-assisted | Robotic imaging system |
| Suturing | Conventional instruments | Laparoscopic instruments | Robotic instruments |
| Recovery | Often longer | Often shorter | Often shorter |
| Selection | Patient-specific | Patient-specific | Patient-specific |
Common Instruments Used in Laparoscopic PUJ Obstruction Surgery
Laparoscopic pyeloplasty requires instruments for visualization, abdominal access, tissue dissection, suturing, urinary drainage, and surgical reconstruction.
The following instruments represent common categories rather than a verified JDMeditech pyeloplasty surgical-set packing list.
1. Laparoscope Telescope
A laparoscope provides visualization of the operative field during minimally invasive surgery.
2. Laparoscopic Camera System
A compatible camera system transmits images from the laparoscope to a surgical monitor.
3. Medical Light Source
A suitable light source provides illumination during the procedure.
4. Fiber-Optic Light Cable
A compatible light cable transfers illumination to the laparoscope.
5. Laparoscopic Trocar
A trocar forms part of a compatible laparoscopic access system.
6. Laparoscopic Cannula
A cannula maintains an access port for suitable laparoscopic instruments.
7. Veress Needle
A Veress needle may be used for selected closed abdominal entry techniques.
8. CO2 Insufflator
A carbon dioxide insufflator maintains pneumoperitoneum during suitable laparoscopic procedures.
9. Laparoscopic Grasping Forceps
Grasping forceps support controlled tissue manipulation.
10. Laparoscopic Dissecting Forceps
Dissecting forceps support selected tissue separation tasks.
11. Maryland Dissector
A Maryland dissector supports fine tissue handling and dissection.
12. Laparoscopic Scissors
Laparoscopic scissors support tissue cutting during reconstruction.
13. Laparoscopic Needle Holder
A laparoscopic needle holder supports intracorporeal suturing during pyeloplasty.
14. Bipolar Forceps
Bipolar forceps support compatible coagulation and bleeding control.
15. Monopolar Electrosurgical Instrument
A compatible monopolar instrument may support selected cutting and coagulation tasks.
16. Suction and Irrigation Cannula
Suction and irrigation equipment helps maintain operative visibility.
17. Double J Ureteral Stent
A Double J stent is commonly placed temporarily to support urine drainage during healing after pyeloplasty.
However, the appropriate stent diameter, length, material, and dwell time depend on patient-specific requirements.
18. Ureteral Guide Wire
A compatible guide wire may support selected stent placement techniques.
19. Ureteral Catheter
A suitable ureteral catheter may be used during selected urinary tract access or drainage procedures.
20. Foley Catheter
A Foley catheter may provide temporary bladder drainage after surgery.
21. Surgical Sutures
Appropriate sutures support reconstruction of the ureteropelvic junction.
22. Surgical Drain
A surgical drain may be placed when indicated to monitor or manage postoperative fluid leakage.
23. Surgical Monitor
A medical-grade monitor displays laparoscopic images for the surgical team.
24. Endoscopy Trolley
A suitable trolley supports organized positioning of visualization equipment.
Laparoscopic Pyeloplasty Instruments and Functions
| Instrument | Primary Function |
|---|---|
| Laparoscope Telescope | Provides surgical visualization |
| Camera System | Transmits images |
| Light Source | Provides illumination |
| Trocar and Cannula | Provide laparoscopic access |
| Veress Needle | Supports selected abdominal entry techniques |
| CO2 Insufflator | Maintains pneumoperitoneum |
| Grasping Forceps | Support tissue manipulation |
| Maryland Dissector | Supports fine tissue dissection |
| Laparoscopic Scissors | Support tissue cutting |
| Needle Holder | Supports reconstructive suturing |
| Bipolar Forceps | Support hemostasis |
| Suction and Irrigation | Support operative visibility |
| Double J Stent | Supports temporary urine drainage |
| Ureteral Guide Wire | Supports selected stent placement techniques |
| Foley Catheter | Supports bladder drainage |
| Surgical Sutures | Support ureteropelvic reconstruction |
How Is Laparoscopic PUJ Obstruction Surgery Performed?
A qualified urologist performs laparoscopic pyeloplasty in an appropriately equipped hospital.
First, the healthcare team evaluates symptoms, kidney function, imaging findings, and suitability for anesthesia.
Next, the patient receives general anesthesia.
During the procedure, the surgeon establishes laparoscopic access and identifies the obstructed ureteropelvic junction.
Depending on the anatomy, the surgeon removes or reconstructs the narrowed segment and reconnects the urinary drainage pathway.
A temporary ureteral stent is often used to support healing.
Finally, the surgeon completes the operation and arranges postoperative monitoring.
However, the exact technique depends on the patient’s anatomy and requires specialist surgical training.
Role of Double J Stents in Pyeloplasty
Double J Ureteral Stents are commonly used during pyeloplasty to maintain temporary urinary drainage across the reconstructed junction.
The curled ends help retain the stent within the urinary tract.
However, stents can cause urinary frequency, discomfort, blood in the urine, or infection.
Furthermore, the stent must be removed or exchanged according to the treating urologist’s plan.
Stent selection should follow the approved intended use and manufacturer instructions.
Potential Benefits of Laparoscopic Pyeloplasty
1. Improved Urine Drainage
Successful reconstruction aims to restore urine flow from the kidney into the ureter.
2. Relief of Flank Pain
Patients with obstruction-related pain may experience symptom improvement after successful surgery.
3. Preservation of Kidney Function
Timely treatment may help preserve remaining kidney function.
4. Smaller Incisions
Laparoscopy generally requires smaller incisions than open surgery.
5. Shorter Hospital Stay
Selected patients may experience a shorter hospital stay than with open surgery.
6. Faster Early Recovery
Minimally invasive surgery may allow earlier return to routine activities.
7. Durable Reconstruction
Pyeloplasty has high reported success rates in appropriately selected patients.
However, no procedure guarantees permanent correction or complete recovery of previously impaired kidney function.
Risks and Complications of Laparoscopic Pyeloplasty
Laparoscopic PUJ obstruction surgery is an invasive procedure with potential complications.
- Bleeding
- Infection
- Urine leakage from the reconstructed junction
- Injury to nearby organs or blood vessels
- Stent-related discomfort
- Persistent or recurrent obstruction
- Anesthesia-related complications
- Blood clots
- Need for additional surgery
Therefore, patients should discuss individual risks and expected outcomes with their urologist.
Recovery After Laparoscopic PUJ Obstruction Surgery
Recovery depends on patient health, surgical complexity, and any postoperative complications.
Many patients undergoing uncomplicated laparoscopic pyeloplasty stay in the hospital for approximately one to two days.
However, some patients require longer observation.
Temporary abdominal discomfort, fatigue, urinary symptoms, or stent-related irritation may occur.
Some patients feel substantially better within one to two weeks, while return to usual activities may take approximately three to four weeks or longer.
Furthermore, heavy lifting and strenuous activity may be restricted for several weeks.
Patients should follow their surgeon’s individualized recovery instructions.
Seek prompt medical attention for fever, severe pain, inability to urinate, persistent vomiting, or significant bleeding.
Follow-Up After Laparoscopic Pyeloplasty
Follow-up is important to confirm satisfactory urinary drainage and monitor kidney function.
The treating team may arrange ureteral stent removal after an appropriate healing period.
Furthermore, ultrasound or a diuretic renal scan may be used to evaluate drainage.
However, imaging schedules and stent removal timing vary according to patient requirements.
Can PUJ Obstruction Return After Surgery?
Yes. PUJ obstruction may recur after pyeloplasty.
For example, scar tissue may cause recurrent narrowing at the reconstructed junction.
However, pyeloplasty has a high overall success rate in appropriately selected patients.
Therefore, follow-up imaging is important, particularly when symptoms return.
How to Choose Laparoscopic PUJ Obstruction Surgical Instruments
Hospitals and urology departments should identify their clinical requirements before purchasing laparoscopic pyeloplasty instruments.
First, determine the planned surgical approach and required visualization system.
Next, review trocar dimensions, graspers, dissecting forceps, scissors, and needle holder specifications.
Furthermore, confirm compatibility between the Double J stent, guide wire, and any required urinary access accessories.
Important Equipment Selection Factors
- Approved intended use
- Complete surgical instrument packing list
- Laparoscope diameter and viewing angle
- Camera and light source compatibility
- Trocar and cannula dimensions
- CO2 insufflator compatibility
- Grasper and dissector working length
- Laparoscopic scissors specifications
- Laparoscopic needle holder design
- Monopolar and bipolar compatibility
- Suction and irrigation compatibility
- Double J stent diameter and length
- Ureteral guide wire compatibility
- Foley catheter requirements
- Reusable or single-use classification
- Cleaning and sterilization instructions
- Manufacturer technical documentation
- Applicable regulatory documentation
Urology and Laparoscopic Instruments by JDMeditech
JDMeditech welcomes inquiries from hospitals, urology departments, laparoscopic surgical centers, and international medical distributors regarding urology instruments and related medical accessories.
Customers can inquire about available Double J stents, ureteral guide wires, laparoscopic instruments, forceps, scissors, needle holders, and compatible accessories.
Furthermore, the JDMeditech team can confirm available product configurations, technical specifications, and applicable documentation for individual inquiries.
For product information and quotations, visit www.jdmeditech.com.
Frequently Asked Questions About Laparoscopic PUJ Obstruction Surgery
1. What is laparoscopic PUJ obstruction surgery?
It is a minimally invasive reconstructive operation used to treat selected cases of narrowing between the renal pelvis and ureter.
2. What does PUJ stand for?
PUJ stands for pelvi-ureteric junction. The same anatomical connection is also called the ureteropelvic junction, or UPJ.
3. What is laparoscopic pyeloplasty?
Laparoscopic pyeloplasty is a minimally invasive operation that reconstructs the obstructed junction to improve urinary drainage.
4. What causes PUJ obstruction?
Causes include congenital narrowing, crossing blood vessels, abnormal ureteral insertion, or acquired scar tissue.
5. What are the symptoms of PUJ obstruction?
Symptoms may include flank pain, urinary infections, nausea, hematuria, or hydronephrosis.
6. Does every PUJ obstruction require surgery?
No. Selected patients can be monitored when kidney function and drainage remain stable.
7. What is Anderson-Hynes pyeloplasty?
It is a reconstructive technique that removes the narrowed junction and reconnects the healthy ureter to the renal pelvis.
8. What is the purpose of a Double J stent?
A Double J stent supports temporary urine drainage during healing after selected pyeloplasty procedures.
9. Is a Double J stent always required?
Not always. Stent use depends on the selected technique and the treating surgeon’s assessment.
10. What instruments are used in laparoscopic pyeloplasty?
Common instruments include laparoscopes, trocars, graspers, Maryland dissectors, scissors, needle holders, and selected urinary drainage accessories.
11. How long does laparoscopic pyeloplasty take?
Many procedures take approximately two to three hours, although duration varies with anatomy and surgical complexity.
12. How long is the hospital stay?
Some patients stay approximately one to two days after uncomplicated surgery, although individual requirements vary.
13. How long does recovery take?
Patients may feel substantially better within one to two weeks, while full return to usual activities may take several weeks.
14. What is the success rate of pyeloplasty?
Published clinical information commonly reports success rates around 90–95% or higher in appropriately selected patients, although outcomes vary.
15. Can PUJ obstruction recur after surgery?
Yes. Recurrent narrowing is possible and may require additional evaluation or treatment.
16. Can kidney function improve after pyeloplasty?
Some patients experience improved drainage or kidney function, but recovery depends on the extent of pre-existing damage.
17. What is the difference between PUJ and UPJ obstruction?
PUJ and UPJ obstruction refer to the same anatomical problem. PUJ means pelvi-ureteric junction, while UPJ means ureteropelvic junction.
18. Where can hospitals inquire about JDMeditech instruments?
Hospitals and distributors can visit JDMeditech to request information about available urology and laparoscopic instruments.
Conclusion
Laparoscopic PUJ Obstruction Surgery is an established minimally invasive treatment option for selected patients with ureteropelvic junction obstruction.
Furthermore, laparoscopic pyeloplasty aims to restore urinary drainage, reduce obstruction-related symptoms, and preserve kidney function.
However, successful treatment requires appropriate patient selection, qualified surgical expertise, compatible medical equipment, and postoperative follow-up.
Contact JDMeditech for urology and laparoscopic surgical instrument inquiries, Double J stents, and related medical accessories, subject to confirmed availability.
Medical Disclaimer: This article provides general educational information only. It does not replace professional medical advice, patient-specific treatment planning, or surgical training. Qualified healthcare professionals must make treatment and equipment decisions according to current clinical guidelines, local regulations, and approved manufacturer instructions.