Introduction to Vesicoureteral Reflux Surgery
Vesicoureteral Reflux Surgery is a urological treatment used for selected patients whose urine flows backward from the bladder toward the ureters and kidneys. Doctors commonly call this condition vesicoureteral reflux, or VUR.
Normally, urine flows from the kidneys through the ureters into the bladder. However, VUR allows urine to move in the opposite direction.
As a result, some patients experience repeated urinary tract infections. Furthermore, kidney infections may cause renal scarring in vulnerable children.
Therefore, doctors evaluate the reflux grade, infection history, bladder function, and kidney health before recommending treatment.
In this guide, JDMeditech explains vesicoureteral reflux, diagnosis, surgical techniques, essential instruments, benefits, risks, recovery, and frequently asked questions.
What Is Vesicoureteral Reflux?
Vesicoureteral reflux is the backward movement of urine from the bladder into one or both ureters. In some cases, urine also reaches the kidneys.
Normally, the connection between the ureter and bladder helps prevent this backward flow.
However, when this natural valve mechanism does not work properly, urine may travel toward the kidney.
Consequently, the child may face an increased risk of urinary infection, especially when additional bladder or bowel problems are present.
Understanding the Urinary System
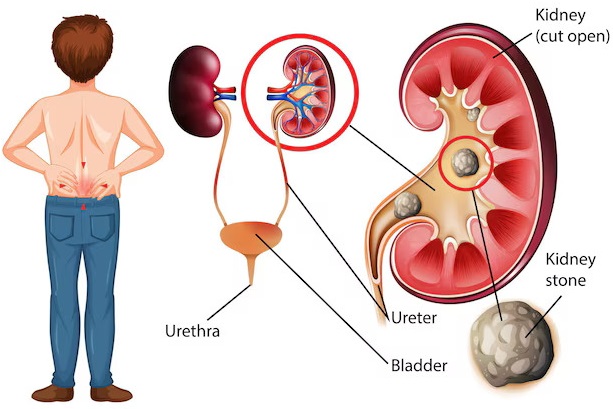
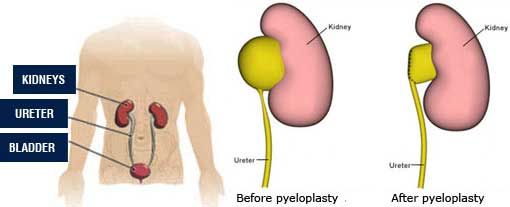
The urinary system includes two kidneys, two ureters, the bladder, and the urethra.
First, the kidneys filter blood and produce urine. Next, the ureters transport urine into the bladder.
Finally, the bladder stores urine until urination.
At the bladder wall, each ureter normally passes through a short tunnel that helps limit backward urine flow.
However, an abnormal junction may allow reflux.
What Causes Vesicoureteral Reflux?
VUR may develop because of congenital anatomy or problems that increase bladder pressure.
1. Primary Vesicoureteral Reflux
Primary VUR usually develops when the ureter-bladder junction does not provide an effective valve mechanism.
Furthermore, the condition often appears in infancy or childhood.
2. Secondary Vesicoureteral Reflux
Secondary VUR develops when bladder dysfunction, obstruction, or increased bladder pressure contributes to backward urine flow.
For example, selected patients with posterior urethral valves or neurological bladder disorders may develop secondary reflux.
3. Family History
VUR can occur in families. Therefore, doctors may consider family history when evaluating urinary symptoms or associated kidney abnormalities.
4. Bladder and Bowel Dysfunction
Constipation, abnormal voiding habits, and incomplete bladder emptying may increase the risk of urinary infections in children with reflux.
Consequently, treating these problems is an important part of care.
Types of Vesicoureteral Reflux
Doctors commonly divide VUR into primary and secondary types.
| Type | Main Cause | Treatment Consideration |
|---|---|---|
| Primary VUR | Developmental difference in the ureter-bladder junction | Observation, infection prevention, or selected surgery |
| Secondary VUR | Bladder dysfunction, obstruction, or elevated bladder pressure | Treatment of the underlying condition |
Vesicoureteral Reflux Grades
Doctors classify VUR into five grades using imaging findings.
Generally, Grade I represents mild reflux, while Grade V represents severe reflux with marked urinary tract dilation.
Grade I Vesicoureteral Reflux
Urine flows backward into the ureter but does not reach the renal pelvis. Additionally, significant urinary tract dilation is absent.
Grade II Vesicoureteral Reflux
Urine reaches the renal pelvis and collecting system without dilation.
Grade III Vesicoureteral Reflux
Reflux causes mild or moderate dilation of the ureter and collecting system.
Grade IV Vesicoureteral Reflux
Moderate dilation develops, and the kidney’s collecting structures become more visibly affected.
Grade V Vesicoureteral Reflux
Severe reflux causes marked dilation and distortion of the ureter and renal collecting system.
Comparison of VUR Grades
| VUR Grade | General Description | Clinical Consideration |
|---|---|---|
| Grade I | Reflux limited to ureter | Often monitored |
| Grade II | Reflux reaches renal pelvis without dilation | May resolve with growth |
| Grade III | Mild to moderate dilation | Requires individual risk assessment |
| Grade IV | Moderate dilation and collecting-system changes | Higher-risk cases may need intervention |
| Grade V | Severe dilation and distortion | Requires careful specialist management |
Common Symptoms of Vesicoureteral Reflux
VUR itself may not cause noticeable symptoms. However, urinary infections can reveal the condition.
For example, some children develop fever, painful urination, or frequent urinary infections.
Common signs and associated problems include:
- Recurrent urinary tract infections
- Fever during urinary infection
- Pain or burning during urination
- Frequent urination
- Urgent need to urinate
- Abdominal discomfort
- Flank pain during kidney infection
- Vomiting or poor feeding in infants
- Urinary incontinence in selected children
- Constipation or bladder dysfunction
- Kidney scarring in higher-risk patients
However, these symptoms are not specific to VUR. Therefore, medical evaluation is necessary.
Vesicoureteral Reflux in Children
VUR is most commonly identified during childhood.
Sometimes, doctors investigate reflux after a febrile urinary tract infection. In other cases, prenatal ultrasound reveals urinary tract dilation that requires follow-up.
Furthermore, children with recurrent infections may need additional testing.
However, not every child with urinary tract dilation has VUR.
Therefore, the healthcare team selects diagnostic tests according to the child’s individual risk.
Vesicoureteral Reflux in Adults
Although VUR is primarily a pediatric condition, some adults have persistent reflux or reflux related to bladder disorders.
For example, an adult may present with recurrent urinary infections or a history of childhood reflux.
Furthermore, bladder dysfunction or obstruction may contribute to secondary VUR.
Therefore, treatment should address the underlying cause and kidney health.
How Is Vesicoureteral Reflux Diagnosed?
Diagnosis involves clinical assessment and suitable urinary tract investigations.
1. Medical History and Physical Examination
The doctor reviews urinary infections, symptoms, family history, bowel habits, and bladder function.
2. Urine Test
Urinalysis and urine culture help identify urinary infection.
3. Renal and Bladder Ultrasound
Ultrasound helps assess kidney size, urinary tract dilation, and bladder appearance.
However, a normal ultrasound does not completely exclude VUR.
4. Voiding Cystourethrogram (VCUG)
A VCUG is an imaging examination used to identify and grade reflux during bladder filling and urination.
Therefore, it is an important diagnostic test when clinically indicated.
5. DMSA Renal Scan
A DMSA scan may help assess kidney cortical abnormalities and scarring in selected patients.
6. Bladder Function Assessment
Selected children need evaluation for abnormal voiding, constipation, or incomplete bladder emptying.
Consequently, doctors can address factors that increase infection risk.
When Is Vesicoureteral Reflux Surgery Recommended?
Not every child with VUR requires surgery.
However, specialists may consider an operation when reflux continues to cause problems despite appropriate treatment.
Possible indications include:
- Frequent breakthrough febrile urinary infections
- Persistent high-grade reflux
- Selected cases with kidney scarring
- High-risk reflux with abnormal kidney findings
- Failure of suitable conservative treatment
- Selected anatomical abnormalities
- Family preference after specialist counseling
Furthermore, doctors consider the child’s age, kidney function, bladder health, and reflux grade.
Therefore, surgical decisions must be individualized.
Treatment Options for Vesicoureteral Reflux
1. Observation and Monitoring
Some mild cases improve naturally as children grow.
Therefore, doctors may recommend follow-up rather than immediate surgery.
2. Antibiotic Treatment
Doctors treat urinary tract infections with appropriate antibiotics.
Additionally, selected children may benefit from preventive low-dose antibiotic treatment.
However, long-term antibiotic use requires careful assessment because resistance and other concerns may arise.
3. Bladder and Bowel Management
Constipation and abnormal voiding habits can increase urinary infection risk.
Therefore, improving bladder emptying and bowel function is an important part of treatment.
4. Endoscopic Injection Treatment
Selected patients undergo endoscopic injection of an approved bulking material near the ureteral opening.
Consequently, the procedure aims to improve the valve mechanism and reduce backward urine flow.
5. Ureteral Reimplantation Surgery
Ureteral reimplantation reconstructs the connection between the ureter and bladder.
Furthermore, the operation creates an effective antireflux mechanism.
What Is Ureteral Reimplantation Surgery?
Ureteral Reimplantation Surgery is a reconstructive procedure used to correct selected cases of vesicoureteral reflux.
The surgeon changes the position or course of the ureter within the bladder wall to improve the natural valve mechanism.
As a result, urine can continue flowing toward the bladder while backward flow is reduced.
However, the technique depends on the patient’s anatomy and clinical needs.
Types of Vesicoureteral Reflux Surgery
1. Open Ureteral Reimplantation
Open surgery uses a conventional incision to reconstruct the ureter-bladder junction.
Furthermore, established open techniques have high success rates in suitable patients.
2. Endoscopic Injection Therapy
Endoscopic treatment uses a cystoscope to visualize the bladder and ureteral opening.
Next, the surgeon injects an approved bulking material at a suitable location.
However, treatment success depends on reflux grade, anatomy, and other clinical factors.
3. Laparoscopic Ureteral Reimplantation
Laparoscopic reconstruction uses a camera and long instruments through small incisions.
However, this approach requires specialist expertise and is not routinely preferred for every patient.
4. Robotic-Assisted Ureteral Reimplantation
Robotic-assisted surgery uses surgeon-controlled instruments for selected reconstructive procedures.
Furthermore, it may help in certain complex cases.
However, outcomes, cost, and complication rates must be considered when selecting this approach.
5. Cohen Cross-Trigonal Reimplantation
Cohen reimplantation is an established intravesical surgical technique.
It creates a longer submucosal ureteral tunnel to improve the antireflux mechanism.
6. Lich-Gregoir Extravesical Reimplantation
Lich-Gregoir reconstruction approaches the ureter-bladder junction from outside the bladder.
However, bilateral procedures require particular attention to the risk of temporary urinary retention.
Comparison of VUR Surgical Techniques
| Technique | Approach | Important Consideration |
|---|---|---|
| Open Reimplantation | Conventional reconstructive surgery | Established high-success treatment |
| Endoscopic Injection | Cystoscopic treatment | Less invasive, but repeat treatment may be needed |
| Laparoscopic Reimplantation | Small incisions and camera | Requires specialist experience |
| Robotic Reimplantation | Robot-assisted reconstruction | Higher equipment demands and variable outcomes |
| Cohen Technique | Intravesical reimplantation | Creates an antireflux ureteral tunnel |
| Lich-Gregoir Technique | Extravesical reimplantation | Requires consideration of postoperative bladder function |
Preparation Before Vesicoureteral Reflux Surgery
Preparation begins with a detailed urological assessment.
First, the surgeon reviews the child’s reflux grade and infection history.
Next, the healthcare team examines kidney health and bladder function.
Furthermore, the doctor explains the proposed treatment and possible complications.
Preparation may include:
- Medical history review
- Physical examination
- Urine testing
- Review of renal ultrasound results
- Review of VCUG findings
- Assessment of kidney scarring when indicated
- Evaluation of bladder and bowel function
- Medication and allergy review
- Anesthesia assessment
- Discussion of treatment alternatives
- Informed consent
- Postoperative care planning
Finally, the healthcare team provides instructions about fasting and hospital admission.
How Is Vesicoureteral Reflux Surgery Performed?
The procedure depends on whether the surgeon selects endoscopic injection or ureteral reimplantation.
First, the surgical team provides suitable anesthesia.
For endoscopic treatment, the surgeon introduces a compatible cystoscope to examine the bladder. Next, the clinician delivers an approved bulking agent near the affected ureteral opening.
For ureteral reimplantation, the surgeon reconstructs the ureter-bladder connection to improve the antireflux mechanism.
Furthermore, the team may use a temporary urinary catheter or drainage device when necessary.
Finally, postoperative monitoring helps assess urine drainage and recovery.
However, the exact steps vary according to the selected technique.
How Long Does VUR Surgery Take?
Operating time depends on the surgical approach and complexity.
For example, endoscopic injection usually requires less operating time than reconstructive ureteral reimplantation.
Furthermore, bilateral procedures may take longer than unilateral operations.
Therefore, the surgeon should provide an individualized estimate.
Essential Instruments Used in Vesicoureteral Reflux Surgery
Vesicoureteral reflux surgical instruments support bladder visualization, precise tissue handling, reconstructive suturing, and urinary drainage.
However, endoscopic injection and open reimplantation require different equipment.
The following list describes general surgical instrument categories. It does not represent a verified JDMeditech VUR surgical set.
1. Pediatric Cystoscope
A suitable pediatric cystoscope provides visualization of the bladder and ureteral openings during selected endoscopic procedures.
2. Cystoscope Telescope
A compatible telescope supports internal visualization.
3. Cystoscope Sheath
A suitable sheath supports compatible endoscopic equipment and fluid management.
4. Endoscopic Camera System
The camera system displays the internal operative field on a monitor.
5. Endoscopic Light Source
A compatible light source provides illumination during cystoscopy.
6. Endoscopic Injection Needle
A suitable injection needle supports delivery of an approved bulking agent during selected procedures.
7. Approved Bulking Agent Delivery System
A compatible delivery system supports administration of an approved injectable material according to its instructions for use.
8. Irrigation Tubing
Suitable irrigation tubing supports fluid flow during endoscopic visualization.
9. Surgical Scalpel
A surgical scalpel supports controlled incision during open reconstructive surgery.
10. Metzenbaum Scissors
Metzenbaum scissors support delicate soft-tissue dissection.
11. Mayo Scissors
Mayo scissors support selected tissue and suture cutting tasks.
12. Fine Surgical Scissors
Fine scissors support controlled cutting during reconstructive procedures.
13. Adson Tissue Forceps
Adson forceps support precise tissue handling.
14. Atraumatic Dissecting Forceps
Atraumatic forceps help surgeons handle delicate tissue gently.
15. Fine Hemostatic Forceps
Fine hemostatic forceps support careful bleeding control.
16. Mosquito Artery Forceps
Mosquito forceps help control small bleeding points.
17. Fine Needle Holder
A fine needle holder supports reconstructive suturing.
18. Mayo-Hegar Needle Holder
A suitable needle holder supports selected wound-closure tasks.
19. Small Surgical Retractor
A compatible retractor helps maintain visibility during open surgery.
20. Self-Retaining Retractor
A suitable self-retaining retractor supports exposure in selected reconstructive procedures.
21. Ureteral Catheter
A compatible ureteral catheter may support selected urinary drainage or imaging requirements.
22. Ureteral Guide Wire
A suitable guide wire may support selected catheter or stent placement procedures.
23. Double J Ureteral Stent
A Double J stent may provide temporary urinary drainage in selected reconstructive cases. However, routine placement is not required for every VUR operation.
24. Foley Urinary Catheter
A suitable Foley catheter supports temporary bladder drainage after selected procedures.
25. Fine Absorbable Sutures
Suitable sutures support delicate tissue reconstruction and wound closure.
26. Laparoscopic Telescope
A laparoscopic telescope provides visualization during selected minimally invasive reimplantation procedures.
27. Laparoscopic Trocar
A compatible trocar provides access for selected laparoscopic instruments.
28. Laparoscopic Grasper
A laparoscopic grasper supports tissue manipulation during minimally invasive reconstruction.
29. Laparoscopic Needle Holder
A laparoscopic needle holder supports reconstructive suturing through small incisions.
30. Suction and Irrigation Instrument
A suitable instrument helps remove fluid and maintain surgical visibility.
31. Bipolar Electrosurgical Forceps
Compatible bipolar forceps may support bleeding control during selected procedures.
32. Electrosurgical Generator
A compatible generator supplies energy to approved electrosurgical instruments.
33. Sterile Surgical Drapes
Sterile drapes help establish the operative field.
34. Sterile Gauze
Sterile gauze supports appropriate wound care and bleeding management.
35. Surgical Dressing
A suitable dressing helps protect the surgical wound.
36. Surgical Instrument Tray
A compatible tray supports instrument organization and reprocessing.
VUR Surgical Instruments and Their Functions
| Instrument | Primary Function | Typical Use |
|---|---|---|
| Pediatric Cystoscope | Bladder visualization | Endoscopic VUR treatment |
| Endoscopic Injection Needle | Bulking agent delivery | Endoscopic injection |
| Endoscopic Light Source | Internal illumination | Cystoscopy |
| Surgical Scalpel | Controlled incision | Open reimplantation |
| Metzenbaum Scissors | Soft-tissue dissection | Open reconstruction |
| Atraumatic Forceps | Gentle tissue handling | Reimplantation |
| Fine Needle Holder | Precise suturing | Ureteral reconstruction |
| Small Retractor | Surgical exposure | Open surgery |
| Ureteral Catheter | Selected drainage support | Reconstructive procedures |
| Double J Stent | Temporary ureteral drainage | Selected cases |
| Foley Catheter | Bladder drainage | Selected postoperative care |
| Laparoscopic Telescope | Internal visualization | Minimally invasive reimplantation |
| Laparoscopic Needle Holder | Reconstructive suturing | Laparoscopic surgery |
Why Is Instrument Selection Important?
VUR surgery may involve delicate pediatric urinary structures.
Therefore, surgeons require equipment that matches the child’s anatomy and selected technique.
Furthermore, cystoscopic injection requires compatible endoscopes, injection needles, and approved materials.
Consequently, hospitals should verify equipment compatibility, intended use, and regulatory documentation before surgery.
Potential Benefits of Vesicoureteral Reflux Surgery
1. Reduction of Backward Urine Flow
Successful treatment aims to reduce or eliminate reflux from the bladder toward the kidneys.
2. Reduced Risk of Recurrent Kidney Infections
Selected patients may experience fewer febrile urinary infections after successful treatment.
3. Protection of Kidney Health
Reducing infection risk may help protect vulnerable kidneys from further injury.
4. Correction of Abnormal Ureteral Anatomy
Ureteral reimplantation reconstructs the ureter-bladder junction to improve the antireflux mechanism.
5. Different Treatment Approaches
Doctors can select observation, endoscopic treatment, or reconstruction according to clinical needs.
Risks and Complications of VUR Surgery
Although VUR procedures are established treatments, complications can occur.
For example, some patients develop temporary urinary symptoms or postoperative discomfort.
Possible complications include:
- Postoperative pain
- Bleeding
- Urinary tract infection
- Wound infection after open surgery
- Temporary difficulty passing urine
- Urinary retention
- Ureteral obstruction
- Persistent or recurrent reflux
- Urine leakage after reconstruction
- Catheter-related discomfort
- Need for repeat injection or surgery
- Anesthesia-related complications
Furthermore, some injection materials have specific risks, including delayed ureteral obstruction.
Therefore, treatment selection and postoperative monitoring are important.
Recovery After Vesicoureteral Reflux Surgery
Recovery depends on the selected treatment.
For example, children undergoing endoscopic injection may recover more quickly than those receiving open reconstruction.
However, individual recovery varies according to age, medical history, and procedure complexity.
Furthermore, some patients need temporary bladder drainage after reimplantation.
Therefore, the healthcare team should provide a personalized recovery plan.
Postoperative Care After VUR Surgery
Appropriate postoperative care supports healing and helps identify complications.
- Give prescribed medicines as directed
- Follow wound-care instructions
- Follow catheter-care instructions when applicable
- Monitor urine output
- Follow fluid-intake recommendations
- Avoid activities restricted by the surgeon
- Attend follow-up appointments
- Complete recommended kidney and bladder imaging
- Monitor for urinary infections
- Continue bladder and bowel management when advised
Additionally, caregivers should contact the healthcare team if urinary symptoms worsen.
How Long Does Recovery Take?
Recovery time varies according to the treatment approach.
Endoscopic injection often involves a shorter recovery period. However, open reconstruction may require additional healing time.
Therefore, the surgeon should provide specific guidance about school, sports, and physical activity.
Can Vesicoureteral Reflux Return After Surgery?
VUR treatment has a high success rate in appropriately selected patients.
However, persistent or recurrent reflux can occur, particularly after endoscopic injection.
Furthermore, some patients may require additional treatment.
Therefore, follow-up depends on the procedure, symptoms, and kidney health.
Does VUR Surgery Prevent All Urinary Infections?
No. Successful correction of reflux does not guarantee that urinary infections will never occur.
For example, constipation, bladder dysfunction, or other urinary conditions may continue to increase infection risk.
Therefore, ongoing urinary health and appropriate medical follow-up remain important.
Does VUR Surgery Reverse Kidney Scarring?
VUR surgery aims to reduce future reflux-related complications.
However, established kidney scars may not disappear after surgery.
Therefore, children with kidney damage may need long-term monitoring of blood pressure, kidney growth, and kidney function.
Why Is Long-Term Follow-Up Important?
Some children require continued monitoring even after successful reflux correction.
For example, patients with previous kidney scarring may need periodic assessment.
Furthermore, clinicians may evaluate recurrent infections, bladder function, and kidney development.
Therefore, the follow-up schedule should reflect the child’s risk factors.
Warning Signs After VUR Surgery
Caregivers should contact the surgical team if concerning symptoms develop.
- Fever or chills
- Severe or worsening abdominal pain
- Persistent vomiting
- Difficulty passing urine
- Little or no urine output
- Increasing wound redness
- Wound discharge
- Heavy bleeding in the urine
- Increasing abdominal swelling
- Problems with a urinary catheter
Importantly, fever with flank pain, inability to pass urine, or signs of serious infection requires urgent medical assessment.
How to Choose VUR Surgical Instruments
Hospitals and pediatric urology departments should identify their procedural requirements before purchasing equipment.
First, purchasing teams should determine whether the facility performs endoscopic injection, open reimplantation, or minimally invasive reconstruction.
Next, they should review suitable cystoscopes, injection needles, fine forceps, scissors, and needle holders.
Furthermore, hospitals should confirm pediatric dimensions and compatibility with approved materials.
Finally, purchasing departments should verify manufacturer instructions, sterilization requirements, and regulatory documentation.
Important Equipment Selection Factors
- Approved intended use
- Pediatric instrument dimensions
- Cystoscope specifications
- Endoscopic camera compatibility
- Light source compatibility
- Injection needle specifications
- Approved bulking agent compatibility
- Fine forceps and scissors dimensions
- Needle holder compatibility
- Suture requirements
- Ureteral catheter dimensions
- Guide wire compatibility
- Urinary drainage requirements
- Reusable or single-use classification
- Cleaning and sterilization instructions
- Applicable regulatory documentation
Vesicoureteral Reflux Surgical Instruments – JDMeditech
JDMeditech welcomes inquiries from hospitals, pediatric urology departments, surgical centers, healthcare institutions, and international medical distributors regarding urological surgical instruments and related medical equipment.
For example, customers can inquire about available cystoscopy instruments, surgical forceps, scissors, needle holders, ureteral catheters, guide wires, and compatible accessories.
Furthermore, healthcare facilities may discuss instrument configuration requirements with the JDMeditech team.
However, customers should confirm product availability, approved intended uses, technical specifications, and applicable regulatory documentation before ordering.
For product information and international business inquiries, visit www.jdmeditech.com.
Frequently Asked Questions About Vesicoureteral Reflux Surgery
1. What is vesicoureteral reflux?
VUR is the backward movement of urine from the bladder toward the ureters and kidneys.
2. What causes VUR?
VUR may result from an abnormal ureter-bladder junction or secondary bladder problems.
3. What are the grades of VUR?
Doctors classify VUR into Grades I through V according to the extent of reflux and urinary tract dilation.
4. Does every child with VUR need surgery?
No. Many children can be monitored or treated without surgery.
5. Can VUR disappear naturally?
Yes. Some children, particularly those with lower-grade reflux, improve as they grow.
6. What is the main risk of VUR?
Recurrent febrile urinary infections and kidney scarring are important concerns in higher-risk patients.
7. How is VUR diagnosed?
Doctors use clinical assessment, urinary tests, and selected imaging such as VCUG.
8. What is a VCUG?
A voiding cystourethrogram is an imaging examination that helps detect and grade urinary reflux.
9. What is ureteral reimplantation?
It is an operation that reconstructs the ureter-bladder junction to reduce backward urine flow.
10. What is endoscopic VUR treatment?
It involves cystoscopic injection of an approved bulking material near the ureteral opening.
11. What is the Cohen technique?
Cohen reimplantation is an established intravesical surgical method that creates a longer antireflux ureteral tunnel.
12. What is Lich-Gregoir reimplantation?
It is an extravesical ureteral reimplantation technique.
13. What instruments are used in VUR surgery?
Common instruments include cystoscopes, compatible injection needles, fine scissors, forceps, needle holders, and urinary drainage accessories.
14. Does VUR surgery require anesthesia?
Yes. Surgical and endoscopic treatments are generally performed under suitable anesthesia.
15. How long does VUR surgery take?
Duration varies according to the surgical technique and complexity.
16. How long does recovery take?
Recovery depends on whether the patient undergoes endoscopic injection or reconstructive surgery.
17. Can reflux return after treatment?
Yes. Persistent or recurrent reflux is possible, especially after some endoscopic treatments.
18. Does surgery prevent every urinary infection?
No. Urinary infections may still occur because of other bladder or urinary conditions.
19. Does VUR surgery reverse kidney scars?
No. Established kidney scarring may remain despite successful reflux correction.
20. Where can hospitals inquire about JDMeditech VUR instruments?
Hospitals and medical distributors can visit JDMeditech to inquire about available urological instruments and accessories.
Conclusion
Vesicoureteral Reflux Surgery is an important treatment option for selected patients with persistent or clinically significant urinary reflux.
Furthermore, endoscopic injection and ureteral reimplantation offer different approaches to correcting backward urine flow.
However, not every patient requires surgery, and treatment decisions depend on kidney health, urinary infections, reflux grade, and bladder function.
Therefore, families should discuss diagnosis, treatment options, possible complications, and follow-up with an experienced pediatric urologist.
For urological surgical instrument inquiries and international business requirements, contact JDMeditech – One Stop for Hospital Needs.
Website: www.jdmeditech.com
Medical Disclaimer: This article provides general educational information only. It does not replace professional medical advice, diagnosis, informed consent, or surgical training. Qualified healthcare professionals must make treatment and equipment decisions according to current clinical guidance, applicable regulations, and approved manufacturer instructions.